Introduction
Understanding how the FDA reviews a 351(k) biosimilar application requires examining a risk-based evaluation framework designed to establish that a proposed biological product is highly similar to an FDA-licensed reference product, with no clinically meaningful differences. The agency evaluates these applications through a stepwise “totality of the evidence” approach, supported by Module 3 comparative analytical characterization, pharmacokinetic/pharmacodynamic (PK/PD) bioequivalence, and multi-tiered immunogenicity assessments. Established under Section 351(k) of the Public Health Service (PHS) Act through the Biologics Price Competition and Innovation Act (BPCI Act) of 2009, this abbreviated licensure pathway enables applicants to rely on the established safety and efficacy profile of an approved reference biologic without necessarily repeating standalone clinical trials.
Biological therapeutics, including recombinant monoclonal antibodies, fusion proteins, and cytokine analogs, are complex, heterogeneous macromolecules produced using microbial or mammalian expression systems. Natural post-translational modifications and variations in cell culture conditions make exact replication of a biologic impossible. Consequently, regulatory approval requires applicants to demonstrate that the biosimilar matches the structural, functional, and clinical performance of the reference product across all relevant levels of characterization. In recent years, the U.S. Food and Drug Administration (FDA) has modernized its evaluation strategy by placing greater statistical emphasis on analytical similarity while reducing the need for comparative clinical efficacy trials in appropriate cases. The following sections explain each tier of evidence reviewed by regulatory scientists during a 351(k) evaluation.
Share via:
Quick Summary:
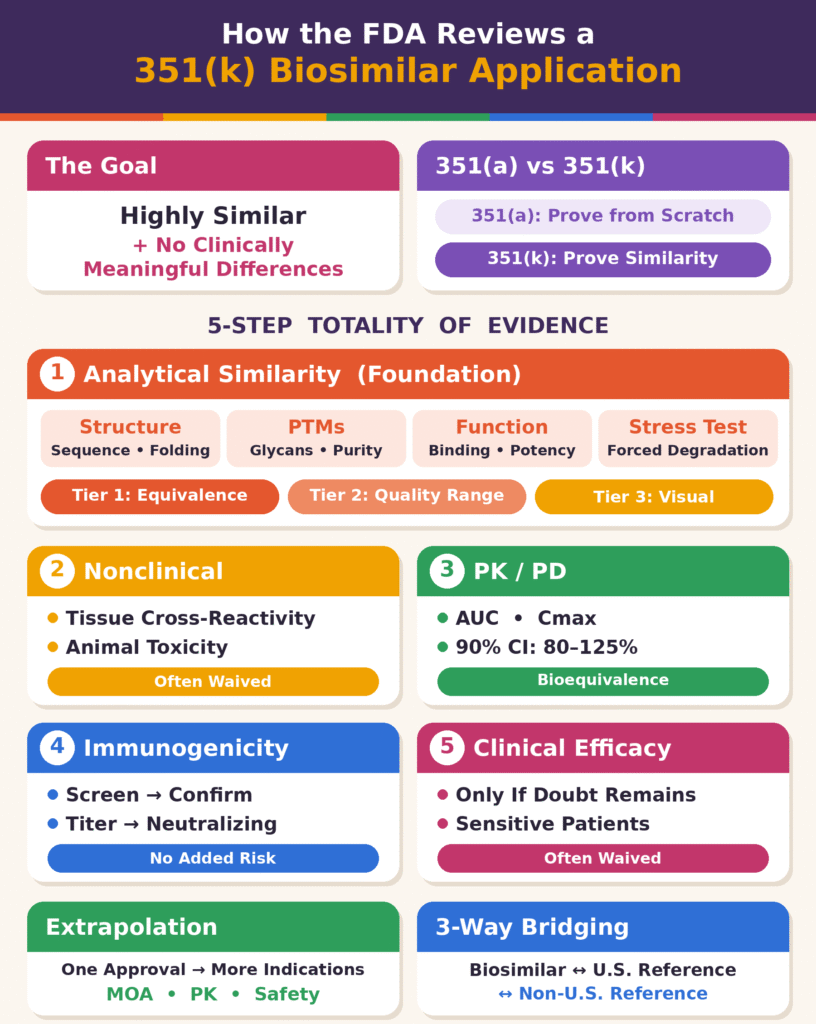
- Pathway basis: Section 351(k) of the PHS Act, created by the BPCI Act of 2009, lets a biosimilar rely on an FDA-licensed reference product’s established safety and efficacy. The applicant does not have to repeat every trial, but it must show the product is highly similar, with no clinically meaningful differences.
- Totality of the evidence: The FDA reviews biosimilars step by step. Analytical, nonclinical, PK/PD, immunogenicity and, if needed, clinical efficacy data are weighed together. Minor, well-characterized differences, such as C-terminal lysine variants, can be acceptable.
- Analytical similarity is the foundation: Head-to-head Module 3 testing compares multiple lots of each product. The tests cover structure, post-translational modifications, purity, function and forced degradation. Results are judged in three statistical tiers: equivalence testing (TOST), quality range, and visual comparison.
- Nonclinical studies are targeted: Tissue cross-reactivity and comparative animal toxicity studies are needed only when analytical uncertainty remains. They are often waived when the analytical data are conclusive.
- PK/PD bioequivalence: Comparative studies, usually crossover or parallel-group, measure AUC and Cmax. The 90% CI of the geometric mean ratio should fall within 80.00–125.00%. PD markers, such as neutrophil count for filgrastim, can add support, and bioanalytical methods must be validated.
- Immunogenicity and efficacy: A four-tier anti-drug antibody strategy (screening, confirmatory, titration, neutralizing) checks that the biosimilar carries no higher immune risk than the reference. Phase III comparative efficacy trials are increasingly waived when analytical and PK/PD evidence leaves no residual uncertainty.
- Extrapolation and bridging: Approval can extend to the reference product’s other indications if mechanism of action, PK and safety are scientifically justified for each. A three-way bridging package allows data generated with a non-U.S. reference product to be used in a U.S. application.
Regulatory Framework: Section 351(k) and the Totality of the Evidence
The regulatory framework governing how the FDA reviews a 351(k) biosimilar application was established under the Biologics Price Competition and Innovation Act (BPCI Act), which introduced Section 351(k) of the Public Health Service (PHS) Act. Under this abbreviated licensure pathway, applicants establish biosimilarity through comparative analytical, nonclinical, and clinical evidence rather than independently repeating all safety and efficacy trials.
For a closer look at the evidence used to establish product similarity, review our guide to biosimilar comparability studies.
Under Section 351(i) of the PHS Act, a biosimilar is defined as a biological product that is highly similar to the reference product, notwithstanding minor differences in clinically inactive components, and has no clinically meaningful differences in terms of safety, purity, and potency. Minor structural variations, such as C-terminal lysine truncations or subtle shifts in glycan distribution, may be acceptable when they are thoroughly characterized and demonstrated to have no clinically meaningful impact.
| Evaluation Parameter | Standalone 351(a) BLA Application | Abbreviated 351(k) Biosimilar Application |
|---|---|---|
| Primary Scientific Objective | Establish independent safety, purity, and potency de novo. | Demonstrate high similarity and the absence of clinically meaningful differences. |
| Data Anchor | Phase III clinical safety and efficacy studies. | Comparative analytical characterization, primarily Module 3 quality data. |
| Preclinical Evaluation | Comprehensive nonclinical toxicity, safety pharmacology, and ADME profiling. | Targeted comparative nonclinical studies, frequently waived when analytical evidence is conclusive. |
| Clinical Pharmacology | Full PK/PD characterization across relevant patient groups. | Comparative PK/PD bioequivalence studies in healthy volunteers or sensitive populations. |
| Clinical Efficacy Testing | Pivotal clinical trials to support the proposed indications, as required. | Streamlined comparative efficacy evaluation, with Phase III trials potentially waived when scientifically justified. |
| Indication Scope | Supported by the clinical and other evidence required for each indication. | May extend to licensed reference product indications through scientifically justified extrapolation. |
Step 1: Comparative Analytical Assessment as the Scientific Foundation
Comparative analytical assessment provides the scientific foundation for evaluating a 351(k) biosimilar application. It uses orthogonal physicochemical and biological assays to establish structural similarity and functional equivalence. Submitted as part of Module 3 of the electronic Common Technical Document (eCTD), the comparative analytical data help determine the nature and extent of any additional nonclinical and clinical testing required by the FDA.
The FDA expects sponsors to conduct head-to-head analytical testing that compares multiple batches of the proposed biosimilar with multiple commercial lots of the U.S.-licensed reference product. This evaluation examines critical quality attributes (CQAs) across primary, secondary, tertiary, and quaternary protein structures, together with biological function and degradation pathways.
Explore how these attributes are prioritized in our overview of critical quality attributes in biosimilars.
| Analytical Tier | Quality Attributes Evaluated | Primary Analytical Methodologies |
|---|---|---|
| Primary Structure and Sequence | Amino acid sequence identity, peptide mapping, and N- and C-terminal sequence integrity. | LC-MS/MS, Edman degradation, and intact/reduced mass spectrometry. |
| Higher-Order Structure (HOS) | Secondary folding, including α-helix and β-sheet structures; tertiary spatial conformation; and disulfide bonding. | Circular Dichroism (CD), FTIR, NMR spectroscopy, and Differential Scanning Calorimetry (DSC). |
| Post-Translational Modifications | Glycosylation profiles, sialylation, core fucosylation, deamidation, and oxidation. | Hydrophilic Interaction Chromatography (HILIC), MALDI-TOF MS, and capillary electrophoresis. |
| Purity and Size Heterogeneity | Soluble aggregates, sub-visible particulates, fragmentation, and charge variants. | SEC-HPLC, Analytical Ultracentrifugation (AUC), CEX-HPLC, and capillary zone electrophoresis. |
| Functional Potency | Target antigen binding, Fc-receptor interactions (FcγR, FcRn, and C1q), and cell-based potency. | Surface Plasmon Resonance (SPR), Bio-Layer Interferometry (BLI), and cell-based reporter bioassays. |
Primary and Higher-Order Structural Characterization
Primary and higher-order structural characterization establishes whether the biosimilar has the same amino acid sequence and comparable secondary, tertiary, and quaternary structures as the reference product. Applicants establish primary sequence identity using tandem liquid chromatography-mass spectrometry (LC-MS/MS) peptide mapping and intact mass analysis. Higher-order structure (HOS) is evaluated using techniques such as circular dichroism (CD), Fourier-transform infrared spectroscopy (FTIR), differential scanning calorimetry (DSC), and nuclear magnetic resonance (NMR) spectroscopy.
See how complementary mass spectrometry methods support structural assessment in our article on native mass spectrometry for biosimilars.
Post-translational modifications (PTMs) require comprehensive profiling because enzymatic and chemical modifications can influence biological half-life, receptor binding, and immunogenicity. Regulatory reviewers pay particular attention to N- and O-linked glycosylation, terminal sialylation, core fucosylation, deamidation, oxidation, and aggregate formation. High-performance size-exclusion chromatography (SEC-HPLC) and analytical ultracentrifugation (AUC) are important methods for quantifying soluble aggregates and characterizing size heterogeneity. Aggregate assessment is particularly important because protein aggregation can contribute to clinical immunogenicity.
For a focused discussion of glycan attributes and their assessment, see our guide to glycosylation analysis of biosimilars.
Functional Activity and Bioassays
Functional bioassays establish whether the proposed biosimilar demonstrates biological activity and target-binding kinetics comparable to those of the reference drug across its known mechanisms of action. Applicants should use orthogonal, complementary bioassays to evaluate the relevant biological activities of the reference product.
- Target Antigen Binding: Quantitative surface plasmon resonance (SPR) or bio-layer interferometry (BLI) is used to measure association (kon) and dissociation (koff) kinetics, as well as equilibrium binding affinity (KD).
- Fc-Receptor Binding Assays: For monoclonal antibodies (mAbs), these assays evaluate binding affinities to FcγRIa, FcγRIIa, FcγRIIIa, including the V158/F158 variants, C1q, and the neonatal Fc receptor (FcRn), which contributes to the regulation of systemic half-life.
- Cell-Based Potency Bioassays: Apoptosis assays, antibody-dependent cellular cytotoxicity (ADCC), complement-dependent cytotoxicity (CDC), and cell proliferation inhibition assays are used to quantify biological activity relative to a reference standard.
Statistical Evaluation Hierarchy and Acceptance Criteria
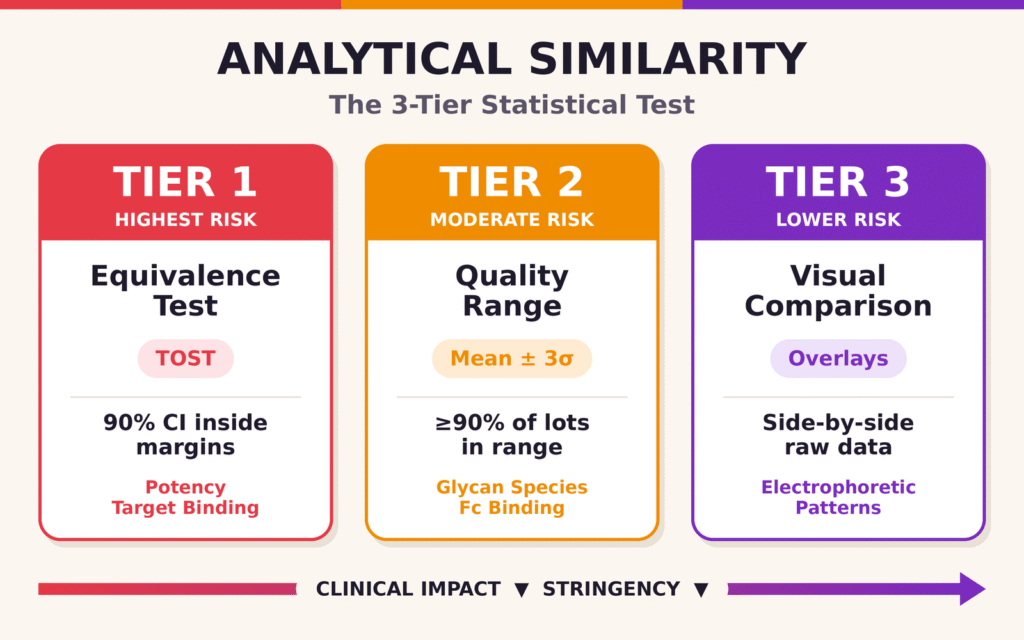
The FDA evaluates analytical similarity using a three-tiered statistical framework based on the clinical relevance of individual quality attributes. Sponsors assign CQAs to the appropriate statistical evaluation tiers before analyzing the data.
For additional context on identifying and assessing product-related impurities, read our guide to impurity profiling of biosimilars.
Tier 1: Equivalence Testing
Tier 1 applies to CQAs with the greatest potential to affect clinical outcomes, such as cell-based potency or primary target binding. It uses Two One-Sided Tests (TOST), with statistical equivalence margins established using the reference product’s standard deviation (σ). Equivalence is demonstrated when the 90% confidence interval for the mean difference falls entirely within the predefined equivalence margins.
Tier 2: Quality Range
Tier 2 applies to CQAs associated with moderate clinical risk, such as specific glycosylation species or secondary binding parameters. The data are evaluated using a Quality Range approach, in which a predefined proportion of biosimilar batch results, typically at least 90%, must fall within an interval established using the reference product mean and a specified number of standard deviations. The multiplier is often set to 3, depending on the attribute and the applicable statistical methodology.
Tier 3: Visual and Raw Data Comparison
Tier 3 applies to CQAs with a lower clinical impact or qualitative characteristics, such as electrophoretic mobility patterns. The results are assessed through side-by-side graphical overlays, raw data comparisons, and descriptive statistics.
Forced Degradation and Stress Profiling
Forced degradation studies determine whether the proposed biosimilar and the reference product exhibit comparable degradation pathways and kinetics when exposed to identical environmental stress conditions. Applicants subject both products to thermal stress, forced photo-oxidation, acid/base hydrolysis, freeze-thaw cycles, and mechanical agitation. These studies help establish whether the degradation pathways, degradant profiles, and stability rates of the biosimilar are consistent with those of the reference formulation.
Review the study design and analytical considerations in our guide to forced degradation of biosimilars.
Step 2: Nonclinical Safety and Animal Toxicity Evaluation
Nonclinical evaluations in a 351(k) application focus on target-tissue binding and comparative animal toxicity when residual analytical uncertainties remain after Module 3 testing. This approach differs from traditional drug development, in which standalone animal safety pharmacology and toxicology studies are commonly integral to the development program.
When regulatory reviewers determine that nonclinical studies are necessary, the investigations generally focus on comparative safety endpoints.
- In Vitro Tissue Cross-Reactivity: Comparative binding studies are conducted using human and animal tissue panels to determine whether the biosimilar and reference product exhibit comparable tissue-reactivity profiles.
- Comparative In Vivo Toxicity: Single-dose or repeat-dose toxicological studies may be conducted in a relevant animal species capable of binding the biological product and exhibiting a pharmacological response. The endpoints generally include toxicokinetics, toxicological target organs, local tolerance, and comparative anti-drug antibody responses.
Under the FDA’s risk-based evaluation approach, animal toxicity studies may be unnecessary when Module 3 analytical characterization establishes a high degree of structural and functional similarity and identifies no concerning novel impurity profiles or unexpected chemical degradants. Such studies may therefore be waived when the available evidence adequately addresses the relevant safety questions.
Step 3: Comparative Clinical Pharmacology and PK/PD Assessment
Comparative clinical pharmacology evaluates the human pharmacokinetic (PK) and pharmacodynamic (PD) profiles of the biosimilar and reference drug to establish bioequivalence. For conventional PK endpoints, the standard acceptance criterion generally requires the 90% confidence interval for the geometric mean ratio (GMR) to fall within 80.00% to 125.00%, subject to the applicable FDA guidance and study-specific requirements.
Clinical PK/PD bioequivalence studies provide a foundational component of the clinical evidence package. They help establish whether the structural and analytical similarity demonstrated in laboratory testing translates into comparable drug exposure and disposition in human subjects.
| Clinical Pharmacology Parameter | Primary Endpoint Focus | Bioequivalence Acceptance Standard |
|---|---|---|
| Systemic Exposure (AUC0–∞) | Area under the plasma concentration-time curve from zero to infinity. | 90% CI of the GMR within 80.00%–125.00%. |
| Extent of Absorption (AUC0–t) | Area under the curve from zero to the last quantifiable time point. | 90% CI of the GMR within 80.00%–125.00%. |
| Peak Exposure (Cmax) | Maximum observed serum concentration following administration of the dose. | 90% CI of the GMR within 80.00%–125.00%. |
| Pharmacodynamic Marker (AUEC/Emax) | Biomarker response over time, such as absolute neutrophil count for filgrastim. | Predefined clinical equivalence bounds, often 80%–125% when appropriate. |
Study Design, Populations, and Parameters
Clinical pharmacology studies are designed to maximize statistical sensitivity to potential differences in drug disposition. The FDA may recommend single-dose, randomized, double-blind, crossover trials in healthy human subjects when the biological product’s safety profile and pharmacological properties make such a design appropriate. However, products with significant toxicity, cytotoxicity, or other safety considerations may require studies in patient populations. When an extended elimination half-life (t1/2) or the risk of immunogenicity following re-exposure makes a crossover design unsuitable, a parallel-group study may be more appropriate.
The principal pharmacokinetic parameters evaluated during regulatory review include total systemic exposure (AUC0–∞), exposure over the sampling interval (AUC0–t), and peak serum concentration (Cmax). Secondary parameters may include time to maximum concentration (Tmax), elimination half-life (t1/2), and apparent clearance (CL/F).
Bioequivalence Acceptance Criteria
To demonstrate clinical PK bioequivalence, the 90% confidence interval (CI) for the ratio of geometric mean exposure measures for the proposed biosimilar and the reference product must generally fall entirely within the standard bioequivalence acceptance interval of 80.00% to 125.00%.
Acceptance Interval:
80.00% ≤ 90% CI of GMR ≤ 125.00%
Here, GMR refers to the ratio of the geometric mean for the biosimilar to that for the reference product.
When a well-characterized pharmacodynamic biomarker is available, comparative PD parameters may be evaluated alongside PK endpoints to provide additional evidence of functional similarity in humans. Examples include absolute neutrophil count (ANC) for filgrastim products and the international normalized ratio (INR) for anticoagulants. Depending on the product and study design, endpoints such as area under the effect curve (AUEC) or maximum effect (Emax) may be assessed.
Bioanalytical Method Validation
Bioanalytical methods used to quantify biological drug concentrations in human serum or plasma, including ELISA, electrochemiluminescence (ECL), and LC-MS/MS, must be appropriately validated. The FDA evaluates these assays for precision, accuracy, selectivity, lower limit of quantitation (LLOQ), target interference, and drug tolerance.
These validation measures help ensure that circulating therapeutic drugs, soluble target receptors, or other interfering substances do not introduce analytical bias when serum concentrations are compared between treatment groups.
Step 4: Multi-Tiered Clinical Immunogenicity Evaluation
Clinical immunogenicity evaluation examines the incidence, titer, and neutralizing capacity of anti-drug antibodies (ADAs) using a validated, multi-tiered assay strategy. The objective is to determine whether the biosimilar presents an immunogenicity risk comparable to that of the reference product. Because therapeutic proteins can trigger unwanted immune responses in human subjects, comparative immunogenicity data form an important component of 351(k) applications.
The purpose of immunogenicity testing is not to demonstrate that the proposed biosimilar is completely non-immunogenic. Instead, the objective is to establish that it does not present a clinically meaningful increase in immunogenicity risk relative to the reference drug. A higher ADA incidence or titer may raise regulatory concerns because it can affect clinical exposure, accelerate drug clearance, neutralize biological activity, or contribute to severe hypersensitivity reactions.
| Testing Tier | Assay Purpose | Technical Execution and Validation Thresholds |
|---|---|---|
| Tier 1: Screening Assay | Broad detection of antibodies that bind to the therapeutic drug. | A high-sensitivity immunoassay designed to maintain an appropriate false-positive rate, often approximately 5%. |
| Tier 2: Confirmatory Assay | Elimination of false-positive results and confirmation of antibody specificity. | Competitive drug inhibition; samples demonstrating inhibition above the predefined cut point are considered positive. |
| Tier 3: Titration Assay | Quantification of relative anti-drug antibody levels. | Serial dilution of confirmed positive samples to determine endpoint ADA titers. |
| Tier 4: Neutralizing Assay (NAb) | Detection of antibodies that directly inhibit the active biological mechanism of action (MOA). | Cell-based bioassays or competitive ligand-binding assays that measure direct neutralization. |
The FDA expects immunogenicity assays used in comparative 351(k) studies to be capable of detecting anti-drug antibodies against both the biosimilar and the reference product. A head-to-head assay strategy with adequate cross-reactivity helps minimize analytical detection bias and supports a reliable comparison of immunogenicity results.
Explore complementary protein-level characterization strategies in our overview of the proteomics approach for biosimilars.
Step 5: Comparative Clinical Efficacy Studies and Modern Regulatory Paradigm Shifts
Comparative clinical efficacy trials are intended to determine whether residual analytical differences between the biosimilar and the reference product have an impact on clinical outcomes. However, modern FDA recommendations increasingly support waiving Phase III comparative efficacy trials when comprehensive analytical and clinical PK/PD evidence adequately addresses the remaining scientific uncertainties.
Historically, comparative Phase III clinical efficacy studies were routinely expected as part of the 351(k) evaluation package. Nevertheless, clinical efficacy trials may be less sensitive to certain minor product differences than advanced analytical techniques, such as mass spectrometry, or appropriately designed clinical PK bioequivalence studies. Clinical endpoints, including overall response rate and progression-free survival, can be influenced by multiple patient-related factors, making subtle product differences more difficult to detect.
Sensitive Study Populations and Clinical Endpoints
When a comparative clinical efficacy trial is considered necessary because residual analytical uncertainty remains, the study should be designed to maximize its ability to identify potential differences between the products.
Population Selection: Applicants should select the most sensitive patient population among those for which the reference product is licensed. The selected population should enable meaningful detection of potential differences while minimizing the influence of confounding factors, such as background therapy, disease characteristics, or immune status, that could obscure differences in efficacy or immunogenicity.
Endpoint Selection: Trial endpoints should focus on sensitive efficacy parameters rather than relying exclusively on long-term clinical outcome measures. Predefined equivalence margins should be scientifically justified using relevant historical clinical data for the reference product. The study should be adequately powered to evaluate whether the observed differences fall within the predefined clinical equivalence margins.
Regulatory Modernization: Streamlining Efficacy Studies
Regulatory recommendations reflect a substantial shift toward streamlining the 351(k) approval process. Updated approaches emphasize that when comprehensive comparative analytical characterization in Module 3, supported by high-resolution clinical PK/PD and immunogenicity assessments, demonstrates a high degree of similarity without residual uncertainty, comparative clinical efficacy trials may provide limited additional scientific value.
When justified by the totality of the evidence and applicable regulatory recommendations, Phase III comparative efficacy studies may therefore be waived. This modern approach can accelerate biosimilar development, reduce unnecessary clinical trial burdens on human participants, and direct scientific resources toward detailed structural characterization, functional assessment, and PK/PD bioequivalence testing.
Scientific Extrapolation and Three-Way Bridging Strategies
Scientific extrapolation can support biosimilar approval for additional licensed indications of the reference product when the available evidence provides an adequate scientific justification. Three-way bridging strategies, meanwhile, allow applicants to use comparative data generated with non-U.S.-licensed reference products when the relevant regulatory requirements are met.
Scientific Justification for Indication Extrapolation
An important advantage of the 351(k) pathway is that sponsors do not necessarily need to conduct separate clinical safety and efficacy trials for every indication licensed for the reference product. Once biosimilarity has been established through an appropriate evidence package, approval may be extrapolated to other requested indications of the reference product when the scientific justification is sufficient.
Learn more about the broader scientific rationale and evidence involved in a biosimilar comparability exercise.
Extrapolation requires a comprehensive scientific assessment that addresses the following considerations:
- Mechanism of Action (MOA): Applicants must establish that the relevant target receptors, active binding sites, and downstream biological pathways are sufficiently similar across the proposed clinical indications.
- Pharmacokinetics and Biodistribution: The assessment should determine whether drug distribution, receptor target expression, and elimination profiles differ meaningfully across patient populations or disease states.
- Immunogenicity and Safety Profiles: Applicants must consider whether different patient populations, such as oncology patients and individuals with autoimmune diseases receiving concomitant immunosuppressants, may exhibit differences in immunogenicity, safety, or toxicity.
Three-Way Bridging Framework
To support global clinical development programs, biosimilar applicants may use non-U.S.-licensed comparator biological products in comparative clinical PK/PD and safety studies. To rely on such data in a U.S. 351(k) submission, the sponsor must provide an appropriate analytical and functional three-way bridging package that establishes the following pairwise comparisons:
- Biosimilar vs. U.S. Reference Product: Head-to-head comparative analytical, functional, and clinical PK/PD evaluations establish the similarity of the biosimilar to the U.S.-licensed reference product.
- Biosimilar vs. Non-U.S. Reference Product: Comparative structural and pharmacokinetic assessments help establish that the biosimilar exhibits comparable biological performance relative to the non-U.S.-licensed reference product.
- U.S. Reference Product vs. Non-U.S. Reference Product: Comparative bridging analyses establish that the U.S.-licensed and non-U.S.-licensed reference biological products are sufficiently similar in their analytical and pharmacokinetic characteristics.
Demonstrating appropriate structural, functional, and PK similarity across all three comparisons provides the scientific justification for using clinical study data generated with a non-U.S.-licensed reference product to support a U.S. 351(k) licensure application. The adequacy of the bridging evidence must be evaluated in the context of the proposed development program and applicable FDA recommendations.
Critical Evaluation Stages in How the FDA Reviews a 351(k) Biosimilar Application
The evaluation process follows a structured, multi-tiered pathway in which regulatory scientists systematically examine evidence relating to product quality, safety, biological activity, and clinical exposure before reaching a licensure determination.
For additional context on biological product quality expectations, consult our overview of the ICH Q6B guidelines for biological characterisation.
| Review Phase | Primary Evaluation Objective | Key Data Inputs and Methodologies | Regulatory Acceptance Standard |
|---|---|---|---|
| Phase 1: Analytical Similarity | Establish structural similarity, higher-order folding, post-translational modifications, and functional potency. | LC-MS/MS, SEC-HPLC, AUC, SPR, cell-based bioassays, and TOST statistical testing. | Demonstration of high similarity, with Tier 1 CQAs meeting the predefined statistical equivalence criteria. |
| Phase 2: Nonclinical Safety | Evaluate potential off-target reactivity, unexpected toxicological findings, and tissue cross-reactivity. | Comparative in vitro tissue-binding studies and repeat-dose toxicokinetic studies in appropriate animal models. | Comparable toxicological profiles; studies may be waived when the analytical evidence adequately addresses relevant uncertainties. |
| Phase 3: Clinical PK/PD Bioequivalence | Establish comparable human exposure, absorption, distribution, and elimination. | Randomized single-dose crossover or parallel-group studies in appropriate human populations. | 90% confidence intervals for the GMRs of AUC0–∞, AUC0–t, and Cmax generally fall within 80.00%–125.00%. |
| Phase 4: Clinical Immunogenicity | Determine whether the biosimilar presents an immunogenicity risk comparable to that of the reference drug. | Multi-tiered ADA testing, including screening, confirmatory, titration, and neutralizing assays. | Comparable ADA/NAb incidence and titers, with no clinically meaningful impact on clearance, efficacy, or safety. |
| Phase 5: Comparative Efficacy, If Needed | Resolve remaining uncertainties about clinical response across patient populations. | Randomized, double-blind, active-controlled clinical trials in sensitive patient populations. | Efficacy endpoints fall within scientifically justified, predefined clinical equivalence margins. |
Conclusion: Mastering How the FDA Reviews a 351(k) Biosimilar Application
Understanding how the FDA reviews a 351(k) biosimilar application requires recognizing that comparative analytical characterization is a central scientific driver of modern biosimilar development and approval. Rather than routinely relying on Phase III clinical outcome trials, the abbreviated 351(k) pathway evaluates the totality of the evidence, including high-resolution structural profiling, orthogonal biological bioassays, clinical PK/PD bioequivalence, and tiered immunogenicity testing.
By establishing a high degree of analytical similarity early in Module 3, biopharmaceutical developers can resolve scientific uncertainties, support indication extrapolation, reduce unnecessary animal testing, and streamline comparative clinical studies when the evidence justifies doing so. As regulatory recommendations continue to evolve, robust analytical characterization remains a fundamental component of an efficient, scientifically sound strategy for obtaining FDA biosimilar licensure.
See how these elements can be assembled into a submission-ready package with our end-to-end biosimilar analytical package for a regulatory submission.
For expert analytical characterization, bioanalytical assay development, and regulatory support, visit the ResolveMass Contact Page.
Frequently Asked Questions
The FDA considers a biological product highly similar when its structural characteristics and biological functions closely resemble those of the reference product, despite minor differences in clinically inactive components. Any identified variations, including differences in post-translational modifications or glycan distribution, must be thoroughly characterized. The evidence must demonstrate that these differences do not result in clinically meaningful changes in safety, purity, or potency.
The totality of the evidence approach involves evaluating all relevant analytical, nonclinical, pharmacokinetic, pharmacodynamic, immunogenicity, and clinical findings collectively. The FDA considers how consistently these data support the proposed biosimilar’s similarity to the reference product. Strong analytical and functional evidence can reduce the need for additional clinical studies when no significant scientific uncertainties remain.
Yes, comparative Phase III efficacy trials may be unnecessary when comprehensive analytical characterization and clinical PK/PD studies adequately establish biosimilarity. The FDA considers whether the available evidence resolves relevant uncertainties regarding safety, efficacy, and biological function. The decision to waive these trials depends on the product’s characteristics, the strength of the evidence, and the remaining scientific questions.
The FDA uses a tiered statistical framework to evaluate differences in critical quality attributes (CQAs) between a biosimilar and its reference product. Tier 1 typically applies equivalence testing using Two One-Sided Tests (TOST), while Tier 2 uses quality ranges for attributes of moderate clinical relevance. Tier 3 generally involves graphical comparisons and descriptive assessments of attributes with lower clinical impact.
Three-way bridging is a comparative strategy used when clinical development involves a non-U.S.-licensed reference product. It evaluates the biosimilar against both the U.S.-licensed and non-U.S.-licensed reference products, while also comparing the two reference products with each other. Appropriate analytical and, where necessary, clinical evidence must support these comparisons to justify using the non-U.S. data in a U.S. submission.
The FDA evaluates immunogenicity through validated assays that detect, confirm, quantify, and assess the neutralizing activity of anti-drug antibodies (ADAs). These investigations determine whether immune responses differ between the biosimilar and its reference product. Reviewers also consider whether antibody formation could affect drug clearance, biological activity, clinical efficacy, or patient safety.
Indication extrapolation allows a biosimilar to receive approval for additional indications of its reference product without requiring separate clinical efficacy trials for every condition. This decision depends on scientific evidence addressing the mechanism of action, pharmacokinetics, safety, immunogenicity, and relevant patient populations. The FDA must determine that the complete evidence package adequately supports the proposed indications.
A biosimilar is a biological product demonstrated to be highly similar to its reference product, with no clinically meaningful differences in safety, purity, and potency. An interchangeable biological product must satisfy additional statutory requirements under U.S. law, including requirements related to the expectation of the same clinical result in any given patient. Interchangeability can permit pharmacy-level substitution, subject to applicable state law and other requirements; additional switching studies are not universally required under current FDA standards.
Bioanalytical assays measure drug concentrations in biological samples, such as serum or plasma, to compare the pharmacokinetic profiles of a biosimilar and its reference product. These methods must be validated for accuracy, precision, selectivity, sensitivity, and potential interference from the drug or soluble targets. Reliable measurements help establish whether systemic exposure is comparable and whether the relevant PK bioequivalence criteria are satisfied.
Reference:
- U.S. Food and Drug Administration. (2015). Quality considerations in demonstrating biosimilarity of a therapeutic protein product to a reference product: Guidance for industry. https://www.fda.gov/media/135612/download
- U.S. Food and Drug Administration. (2021). Development of therapeutic protein biosimilars: Comparative analytical assessment and other quality-related considerations: Guidance for industry. https://www.fda.gov/media/159261/download
- Hung, A., Vu, Q., & Mostovoy, L. (2017). A systematic review of U.S. biosimilar approvals: What evidence does the FDA require and how are manufacturers responding? Journal of Managed Care & Specialty Pharmacy, 23(12), 1234–1244. https://doi.org/10.18553/jmcp.2017.23.12.1234
- Scheibner, K. A. (2022, July 19). Immunogenicity and biosimilars: Moving from small to large molecules [Workshop presentation]. U.S. Food and Drug Administration, Office of Study Integrity and Surveillance Workshop 2022. https://www.fda.gov/media/166006/download
- U.S. Food and Drug Administration. (2015, April 28). Scientific considerations in demonstrating biosimilarity to a reference product: Guidance for industry. https://www.fda.gov/media/82647/download
Get In Touch With Us
About The Author